Measure Information Form
Version 2027A
Measure Information Form
| Set Measure ID | Performance Measure Name |
|---|---|
CSTK-05a  |
Hemorrhagic Transformation for Patients Treated with Intra-Venous (IV) Alteplase Therapy Only |
| CSTK-05b |
Hemorrhagic Transformation for Patients Treated with Intra-Arterial (IA) Alteplase Therapy or Mechanical Endovascular Reperfusion Therapy |
CSTK-05 Ischemic stroke patients who develop a symptomatic intracranial hemorrhage (i.e., clinical deterioration ≥ 4 point increase on NIHSS and brain image finding of parenchymal hematoma, or subarachnoid hemorrhage, or intraventricular hemorrhage) within (≤) 36 hours after the onset of treatment with intra-venous (IV) or intra-arterial (IA) alteplase therapy, or mechanical endovascular reperfusion procedure (i.e., mechanical endovascular thrombectomy with a clot retrieval device). CSTK-05a Ischemic stroke patients who develop a symptomatic intracranial hemorrhage (i.e., clinical deterioration ≥ 4 point increase on NIHSS and brain image finding of parenchymal hematoma, or subarachnoid hemorrhage, or intraventricular hemorrhage) within (≤) 36 hours after the onset of treatment with intra-venous (IV) alteplase therapy only. CSTK-05b Ischemic stroke patients who develop a symptomatic intracranial hemorrhage (i.e., clinical deterioration ≥ 4 point increase on NIHSS and brain image finding of parenchymal hematoma, or subarachnoid hemorrhage, or intraventricular hemorrhage) within (≤) 36 hours after the onset of treatment with IA alteplase therapy or mechanical endovascular reperfusion therapy (i.e., mechanical endovascular thrombectomy with a clot retrieval device).
The CSTK-05 measure is reported as an overall rate which includes ischemic stroke patients who develop a symptomatic hemorrhage after reperfusion therapy. CSTK-05a and CSTK-05b are subsets of the overall rate, and stratified by the type of therapy.
Rationale: Intravenous (IV) alteplase therapy for acute ischemic stroke was approved by the US Food and Drug Administration in 1996, following findings from the National Institute of Neurological Disorders and Stroke (NINDS) trial which demonstrated favorable outcomes in 31% to 50% of patients treated with recombinant tissue plasminogen activator (r-tPA), as compared to 20% to 38% of patients treated with placebo. Intracranial hemorrhage is the major risk of thrombolytic therapy with similar rates reported for both IV and IA routes. The NINDS trialists found that 6.4% of patients treated with IV alteplase experienced symptomatic bleeding. In the NINDS trials, suspicion of hemorrhage within 36 hours of treatment not previously noted on head CT or any decline in neurological status was considered a complication of therapy (von Kummer, et al., 2015). Findings from the Prolyse in Acute Cerebral Thromboembolism (PROACT II) study found the intracranial hemorrhage with neurological deterioration within 24 hours occurred in 10% of patients treated with IA recombinant prourokinase. More recent clinical trials and prospective stroke registries report 2%-7% incidence of sICH after alteplase, (Yaghi, S., et al., 2017).Endovascular reperfusion therapy in acute ischemic stroke comprises a number of pharmacological and mechanical procedures. Mechanical endovascular thrombectomy is a treatment option for patients with large vessel occlusions in whom pharmacological thrombolysis is contraindicated or might be ineffective. For eligible patients, initiation of EVT (e.g., groin puncture) within 6 hours of stroke symptom onset using a stent retriever is preferred (Powers, W.J., et al., 2015). The use of mechanical thrombectomy devices other than stent retrievers as first-line devices for mechanical thrombectomy may be reasonable in some circumstances (Powers W.J., et al., 2018). Mechanical endovascular thrombectomy devices are intended to improve tissue rescue and diminish reperfusion hemorrhage while broadening the population eligible for therapy. These devices may be used alone or in conjunction with chemical thrombolysis (i.e., IV or IA alteplase).
Over the last decade, mechanical thrombectomy (MT) has become the standard of care for the treatment of acute ischemic stroke caused by large vessel occlusions (LVO). Clinical studies have reported sICH rates between 3.6% and 9.3% following MT, (Hall, E., et al., 2024). Higher rates up to 16% have been reported in real-world practice. The risk of sICH varies significantly based on the location and severity of the initial stroke with higher risk and more severe hemorrhages (i.e., intraventricular and large parenchymal) generally reported for EVT in proximal vessels (e.g., ICA). However, one recent meta-analysis reported higher risk associated with MT in the posterior circulation (RR: 7.48; 95% CI: 2.27-24.61 vs RR: 1.18; 95%CI: 0.90—1.56 )(p=0.003), (Reda, A., et al., 2025).
Symptomatic intracranial hemorrhage following reperfusion is a clinical event and potentially critical complication of therapy. The Heidelberg Classification uses both brain imaging to distinguish between hemorrhagic infarction (HI) and parenchymatous hematoma (PH), as well as, changes in NIHSS score to assess neurological deterioration (i.e., >/= 4 point increase). HI 1 and HI 2 are defined as petechial hemorrhages without space-occupying effect; PH 1 and PH 2 are solid clots in the area of infarction with space-occupying effect. PH 2 classification represents a larger blood clot and is associated with increased mortality at 90-days post-ischemic stroke (von Kummer, et al., 2015).
Type Of Measure: Outcome Improvement Noted As: Decrease in the rateCSTK-05 Ischemic stroke patients who develop a symptomatic intracranial hemorrhage ≤ 36 hours after the onset of treatment with IV alteplase therapy, or IA alteplase therapy, or mechanical endovascular reperfusion therapy CSTK-05a Ischemic stroke patients who develop a symptomatic intracranial hemorrhage ≤ 36 hours after the onset of treatment with IV alteplase therapy only (IVO) CSTK-05b Ischemic stroke patients who develop a symptomatic intracranial hemorrhage ≤ 36 hours after the onset of treatment with IA alteplase therapy or mechanical endovascular reperfusion therapy
Included Populations: As above Excluded Populations: None Data Elements:Data Elements By Measure
- Arrival Date
- Arrival Time
- Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation
- Highest NIHSS Score Documented Within 36 Hours Following IV Alteplase Initiation
- IA Alteplase or MER Initiation Date
- IA Alteplase or MER Initiation Time
- IA Route of Alteplase Administration
- IV Alteplase Initiation
- IV Alteplase Initiation Date
- IV Alteplase Initiation Time
- NIHSS Score Documented Closest to IA Alteplase or MER Initiation
- NIHSS Score Documented Closest to IV Alteplase Initiation
- Positive Brain Image
- Positive Brain Image Date
- Positive Brain Image Time
| CSTK-05 | CSTK-05a | CSTK-05b |
|---|---|---|
| Arrival Date | Arrival Date | Arrival Date |
| Arrival Time | Arrival Time | Arrival Time |
| Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation | Highest NIHSS Score Documented Within 36 Hours Following IV Alteplase Initiation | Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation |
| Highest NIHSS Score Documented Within 36 Hours Following IV Alteplase Initiation | IV Alteplase Initiation | IA Route of Alteplase Administration |
| IA Route of Alteplase Administration | IV Alteplase Initiation Date | IA Alteplase or MER Initiation Date |
| IA Alteplase or MER Initiation Date | IV Alteplase Initiation Time | IA Alteplase or MER Initiation Time |
| IA Alteplase or MER Initiation Time | NIHSS Score Documented Closest to IV Alteplase Initiation | NIHSS Score Documented Closest to IA Alteplase or MER Initiation |
| IV Alteplase Initiation | Positive Brain Image | Positive Brain Image |
| IV Alteplase Initiation Date | Positive Brain Date | Positive Brain Image Date |
| IV Alteplase Initiation Time | Positive Brain Image Time | Positive Brain Image Time |
| NIHSS Score Documented Closest to IA Alteplase or MER Initiation | ||
| NIHSS Score Documented Closest to IV Alteplase Initiation | ||
| Positive Brain Image | ||
| Positive Brain Image Date | ||
| Positive Brain Image Time |
Included Populations:Excluded Populations:
- Discharges with ICD-10-CM Principal Diagnosis Code for ischemic stroke as defined in Appendix A, Table 8.1 for ICD-10 codes,
AND- Patients with documented thrombolytic (IV or IA alteplase) therapy (ICD-10-PCS Principal or Other Procedure Codes as defined in Appendix A, Table 8.1a for ICD-10 codes ),
OR- Patients with documented Mechanical Endovascular Reperfusion Therapy (ICD-10-PCS Principal or Other Procedure Codes as defined in Appendix A, Table 8.1b for ICD-10 codes)
Data Elements:
- Patients less than 18 years of age
- Patients who have a Length of Stay > 120 days
- Patients admitted for Elective Carotid Intervention
- Patients transferred to this hospital following treatment with IV alteplase therapy or IA alteplase therapy or mechanical endovascular reperfusion therapy initiated prior to arrival at this hospital
- Patients who hemorrhage prior to the onset of treatment with IV alteplase or IA thrombolytic alteplase or mechanical endovascular reperfusion therapy
- Campbell, B. C. V., Mitchell, P. J., Kleinig, T. J., Dewey, H. M., Churilov, L., Yassi, N., et al. (2015). Endovascular therapy for ischemic stroke with perfusion imaging selection. The New England Journal of Medicine, 372 (11), 1009–1017.
- Demchuk, A. M., Goyal, M., Menon, B. K., Eesa, M., Ryckborst, K. J., Kamal, N., et al. (2015). Endovascular treatment for small core and anterior circulation proximal occlusion with emphasis on minimizing CT to recanalization times (ESCAPE) trial: Methodology. International Journal of Stroke, 10 (3), 429–438.
- Hall, E., Ullberg, T., Andsberg, G., & Wasselius, J. (2024). Incidence of intracranial hemorrhagic complications after anterior circulation endovascular thrombectomy in relation to occlusion site: A nationwide observational register study. Journal of NeuroInterventional Surgery, 16 (11), 1088–1093. https://doi.org/10.1136/jnis-2023-020768
- Leifer, D., Bravata, D. M., Connors, J. J., III, Hinchey, J. A., Jauch, E. C., Johnston, S. C., Latchaw, R., Likosky, W., Ogilvy, C., Qureshi, A. I., Summers, D., Sung, G. Y., Williams, L. S., & Zorowitz, R., on behalf of the American Heart Association Special Writing Group of the Stroke Council, Atherosclerotic Peripheral Vascular Disease Working Group and Council on Cardiovascular Surgery and Anesthesia, and Council on Cardiovascular Nursing. (2011). Metrics for measuring quality of care in comprehensive stroke centers: Detailed follow-up to Brain Attack Coalition comprehensive stroke center recommendations: A statement for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 42, 853-54.
- Menon, B. K., Saver, J. L., Prabhakaran, S., Reeves, M., Liang, L., Olson, D. W. M., Peterson, E. D., Hernandez, A. F., Fonarow, G. C., Schwamm, L. H., & Smith, E. E. (2012). Risk score for intracranial hemorrhage in patients with acute ischemic stroke treated with intravenous tissue type plasminogen activator. Stroke, 43, 1–9.
- Powers, W. J., Derdeyn, C. P., Biller, J., Coffey, C. S., Jauch, E. C., Johnston, K. C., Johnston, S. C., Khalessi, A. A., Kidwell, C. S., Meschia, J. F., Ovbiagele, B., & Yavagal, D. R., on behalf of the American Heart Association Stroke Council. (2015). 2015 AHA/ASA focused update of the 2013 guidelines for the early management of patients with acute ischemic stroke regarding endovascular treatment: A guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 46, 3021–3035.
- Powers, W. J., Rabinstein, A. A., Ackerson, T., Adeoye, O. M., Bambakidis, N. C., Becker, K., Biller, J., et al., on behalf of the American Heart Association Stroke Council. (2018). 2018 guidelines for the early management of patients with acute ischemic stroke: A guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 49, e10–e11, e18–e30.
- Powers, W. J., Rabinstein, A. A., Ackerson, T., Adeoye, O. M., Bambakidis, N. C., Becker, K., Biller, J., et al. (2019). Guidelines for the early management of patients with acute ischemic stroke: 2019 update to the 2018 guidelines for the early management of acute ischemic stroke—A guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 50 (12), e344–e418.
- Reda, A., Hasanzadeh, A., Ghozy, S., Sanjari Moghaddam, H., Adl Parvar, T., Motevaselian, M., Kadirvel, R., Kallmes, D. F., & Rabinstein, A. (2025). Risk of symptomatic intracranial hemorrhage after mechanical thrombectomy in randomized clinical trials: A systematic review and meta-analysis. Brain Sciences, 15 (1), Article 63. https://doi.org/10.3390/brainsci15010063
- Saver, J. L., Goyal, M., Bonafe, A., Diener, H.-C., Levy, E. I., Pereira, V. M., et al. (2015). Stent retriever thrombectomy after intravenous t PA vs. t PA alone in stroke. The New England Journal of Medicine, 372 (24), 2285–2295.
- von Kummer, R., Broderick, J. P., Campbell, B. C. V., Demchuk, A., Goyal, M., Hill, M. D., Treurniet, K. M., Majoie, C. B. L. M., Marquering, H. A., Mazya, M. V., San Román, L., Saver, J. L., Strbian, D., Whiteley, W., & Hacke, W. (2015). The Heidelberg bleeding classification: Classification of bleeding events after ischemic stroke and reperfusion therapy. Stroke, 46 (10), 2981–2986. https://doi.org/10.1161/STROKEAHA.115.010049
- Yaghi, S., Willey, J. Z., Cucchiara, B., Goldstein, J. N., Gonzales, N. R., Khatri, P., Kim, L. J., Mayer, S. A., Sheth, K. N., & Schwamm, L. H. (2017). Treatment and outcome of hemorrhagic transformation after intravenous alteplase in acute ischemic stroke: A scientific statement for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 48 (12), e343–e361. https://doi.org/10.1161/STR.0000000000000152


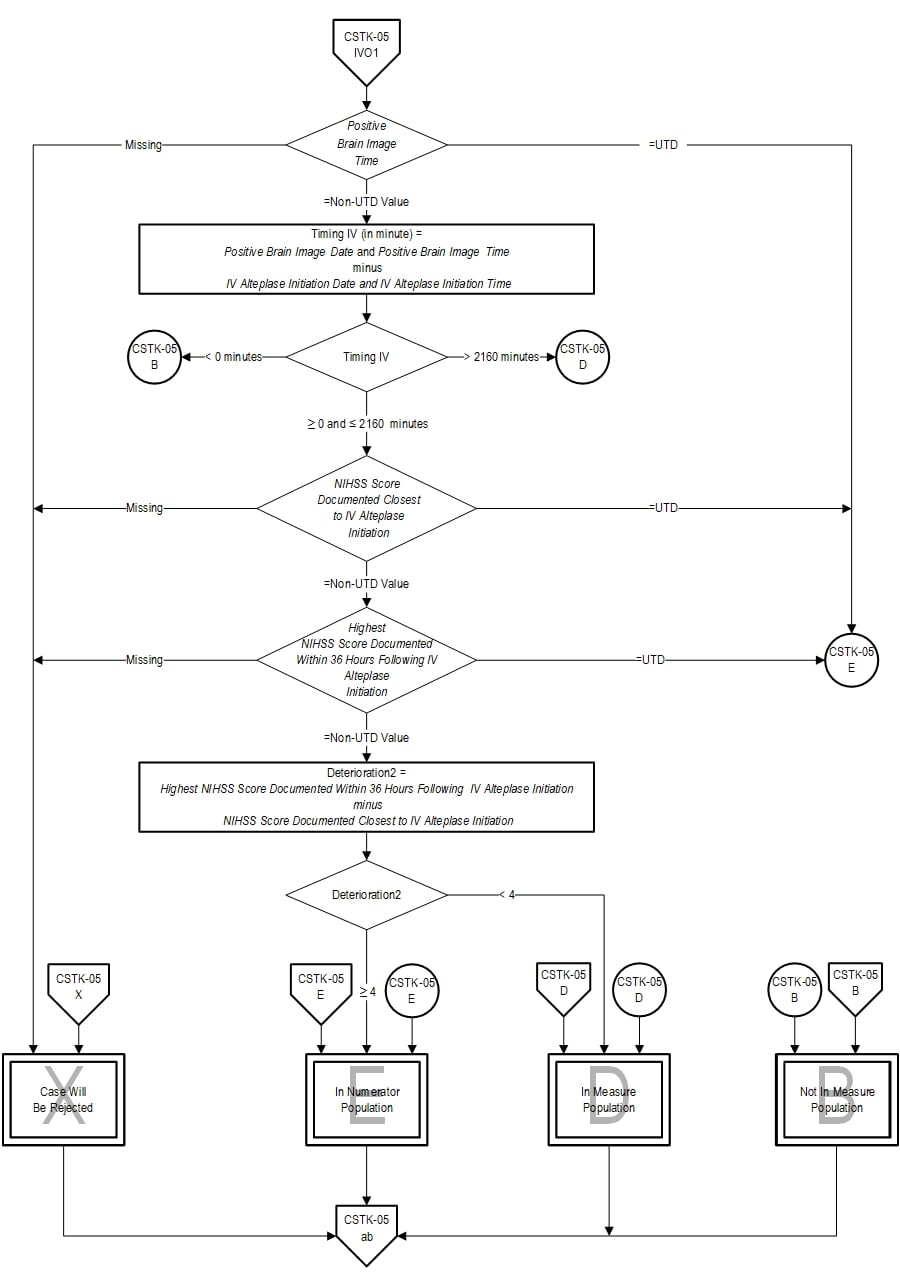
CSTK-05: Algorithm Narrative
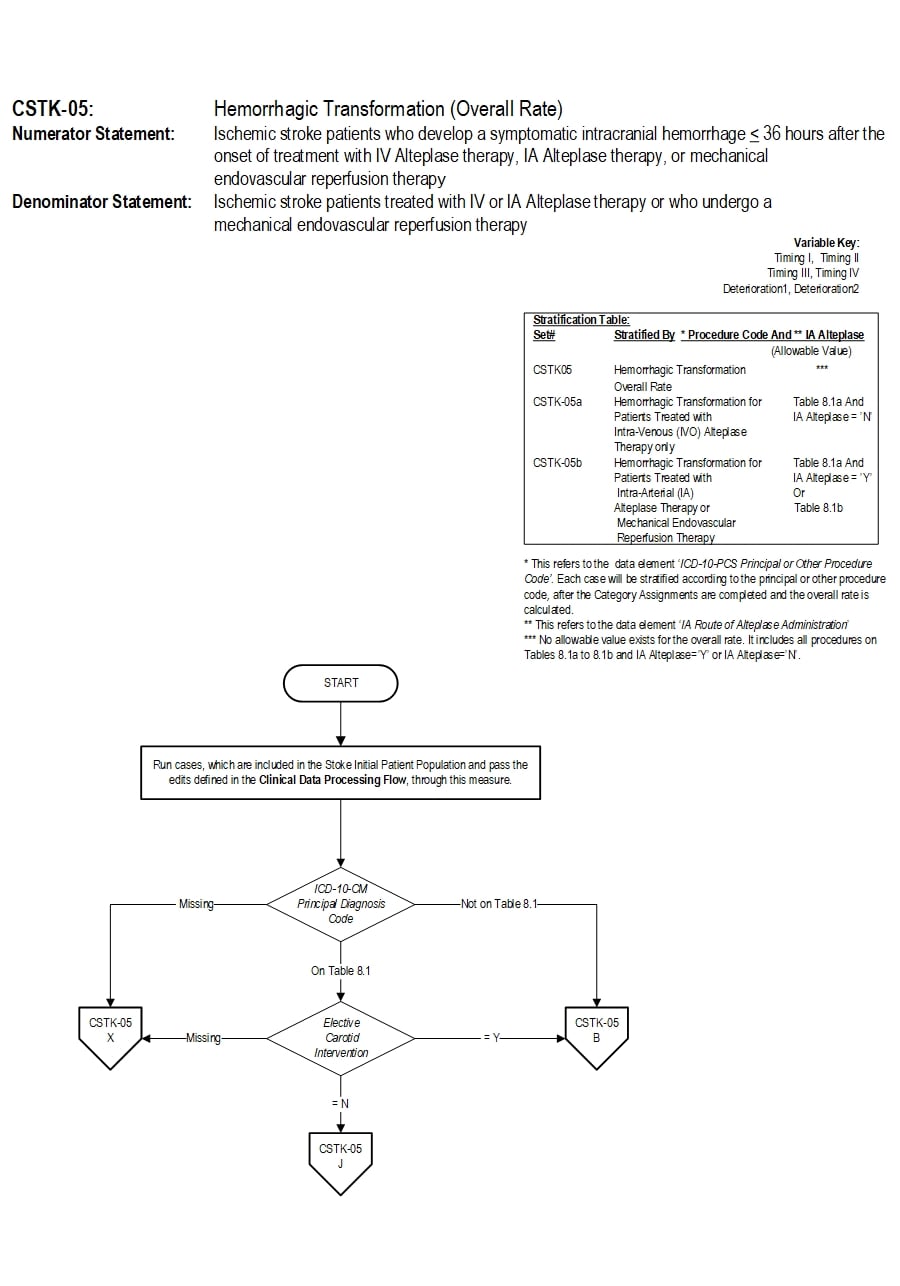
CSTK-05: Hemorrhagic Transformation (Overall Rate) Numerator Statement: Ischemic stroke patients who develop a symptomatic intracranial hemorrhage less than or equal to 36 hours after the onset of treatment with IV alteplase therapy, IA alteplase therapy, or mechanical endovascular reperfusion therapy
Denominator Statement: Ischemic stroke patients treated with IV or IA alteplase therapy or who undergo a mechanical endovascular reperfusion therapy
Variable Key:
Timing I, Timing II, Timing III, Timing IV
Deterioration1, Deterioration2
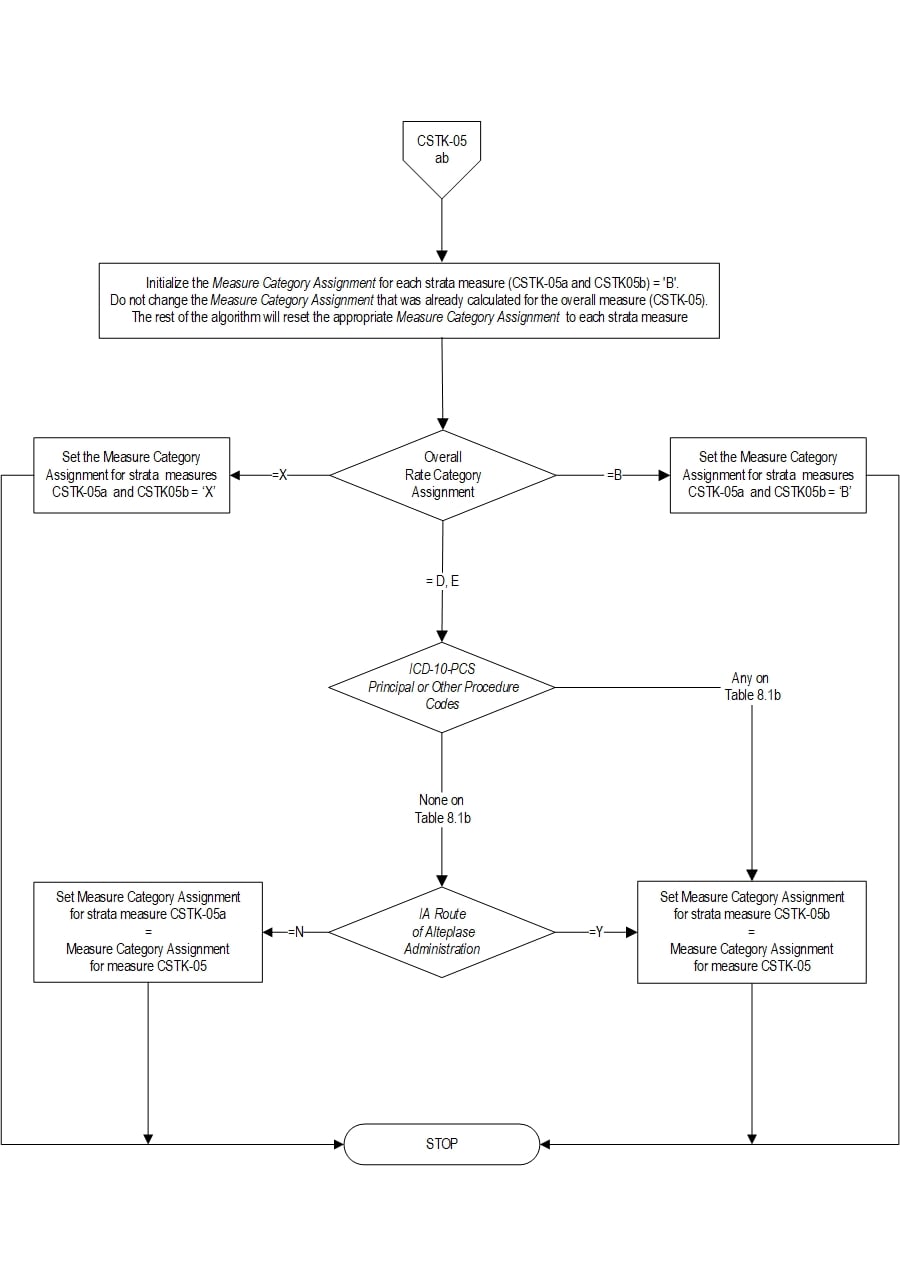
Stratification Table:Each case will be stratified according to the principal or other procedure code, after the Category Assignments are completed and the overall rate is calculated.
CSTK05 is Hemorrhagic Transformation Overall Rate.
CSTK-05a is each case of Hemorrhagic Transformation with procedures on Tables 8.1a and Intra-Arterial (IA) Route of Alteplase Administration equals 'N', and alteplase administration route is Intra-Venous (IVO).
CSTK-05b is each case of Hemorrhagic Transformation with procedures on Tables 8.1a and Intra-Arterial (IA) Route of Alteplase Administration equals 'Y' or with procedures on Tables 8.1b Mechanical Endovascular Reperfusion Therapy.
1. Start processing. Run cases, which are included in the Comprehensive Stoke Initial Patient Population and pass the edits defined in the Clinical Data Processing Flow, through this measure.
2. Check ICD-10-CM Principal Diagnosis Code
- If all ICD-10-CM Principal Diagnosis Codes are missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If none of the ICD-10-CM Principal Diagnosis Codes are on Table 8.1, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If at least one of the ICD-10 CM Principal Diagnosis codes is on Table 8.1, continue processing and proceed to check Elective Carotid Interventions.
- If Elective Carotid Intervention is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Elective Carotid Intervention equals Y, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If Elective Carotid Intervention equals N continue processing and proceed to check ICD-10-PCS Principal or Other Procedure Codes.
- If all ICD-10-PCS Principal or Other Procedure Codes are missing or none of them on Table 8.1a or 8.1b, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If at least one of the ICD-10-PCS Principal or Other Procedure Codes is on Table 8.1a or 8.1b, the case will proceed to step 5 to check ICD-10-PCS Principal or Other Procedure Codes.
- If at least one of the ICD-10-PCS Principal or Other Procedure Codes is on Table 8.1b, the case will proceed to step 7 to check IA Alteplase or MER Initiation Date
- If none of the ICD-10-PCS Principal or Other Procedure Codes are on Table 8.1b, the case will proceed to step 6 to check IA Route of Alteplase Administration.
- If IA Route of Alteplase Administration equals Y, the case will proceed to step 7 to check IA Alteplase or MER Initiation Date.
- If IA Route of Alteplase Administration equals N, the case will proceed to step 22 to check IV Alteplase Initiation.
- If IA Alteplase or MER Initiation Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If IA Alteplase or MER Initiation Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If IA Alteplase or MER Initiation Date is Non-UTD value continue processing and proceed to check IA Alteplase or MER Initiation Time.
- If IA Alteplase or MER Initiation Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If IA Alteplase or MER Initiation Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If IA Alteplase or MER Initiation Time is Non-UTD value continue processing to check Arrival Date.
- If Arrival Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Arrival Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Arrival Date is Non-UTD value continue processing and proceed to check Arrival Time.
- If Arrival Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Arrival Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Arrival Time is Non-UTD value continue processing to calculate Timing I.
- Timing I (in minute) equal IA Alteplase or MER Initiation Date and IA Alteplase or MER Initiation Time minus Arrival Date and Arrival Time.
- Proceed to Check Timing I (in minutes).
- If timing I is less than 0 minutes, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If timing I is equal to or greater than 0 minutes, continue processing and proceed to check Positive Brain Image.
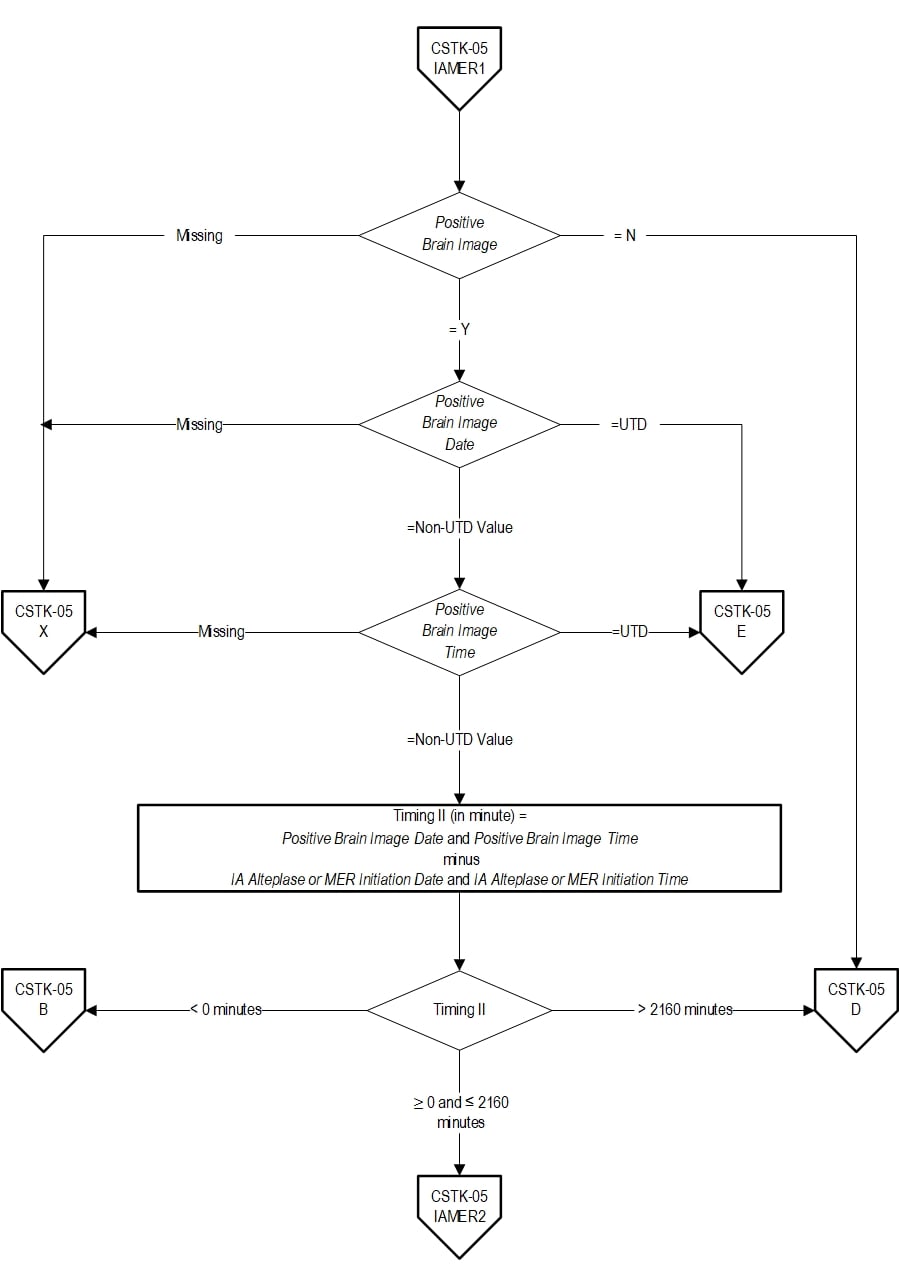
- If Positive Brain Image is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image equals N, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Positive Brain Image equals Y, continue processing to check Positive Brain Image Date.
- If Positive Brain Image Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Positive Brain Image Date is Non-UTD value continue processing and proceed to check Positive Brain Image Time.
- If Positive Brain Image Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Positive Brain Image Time is Non-UTD value continue processing to calculate Timing II.
- Timing II (in minute) equals Positive Brain Image Date and Positive Brain Image Time minus IA Alteplase or MER Initiation Date and IA Alteplase or MER Initiation Time.
- Proceed to Check Timing II (in minutes).
- If Timing II is less than 0 minutes, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If Timing II is greater than 2160 minutes, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Timing II is equal or greater than 0 minutes and equal or less than 2160 minutes, continue processing and proceed to check NIHSS Score Documented Closest to IA Alteplase or MER Initiation.
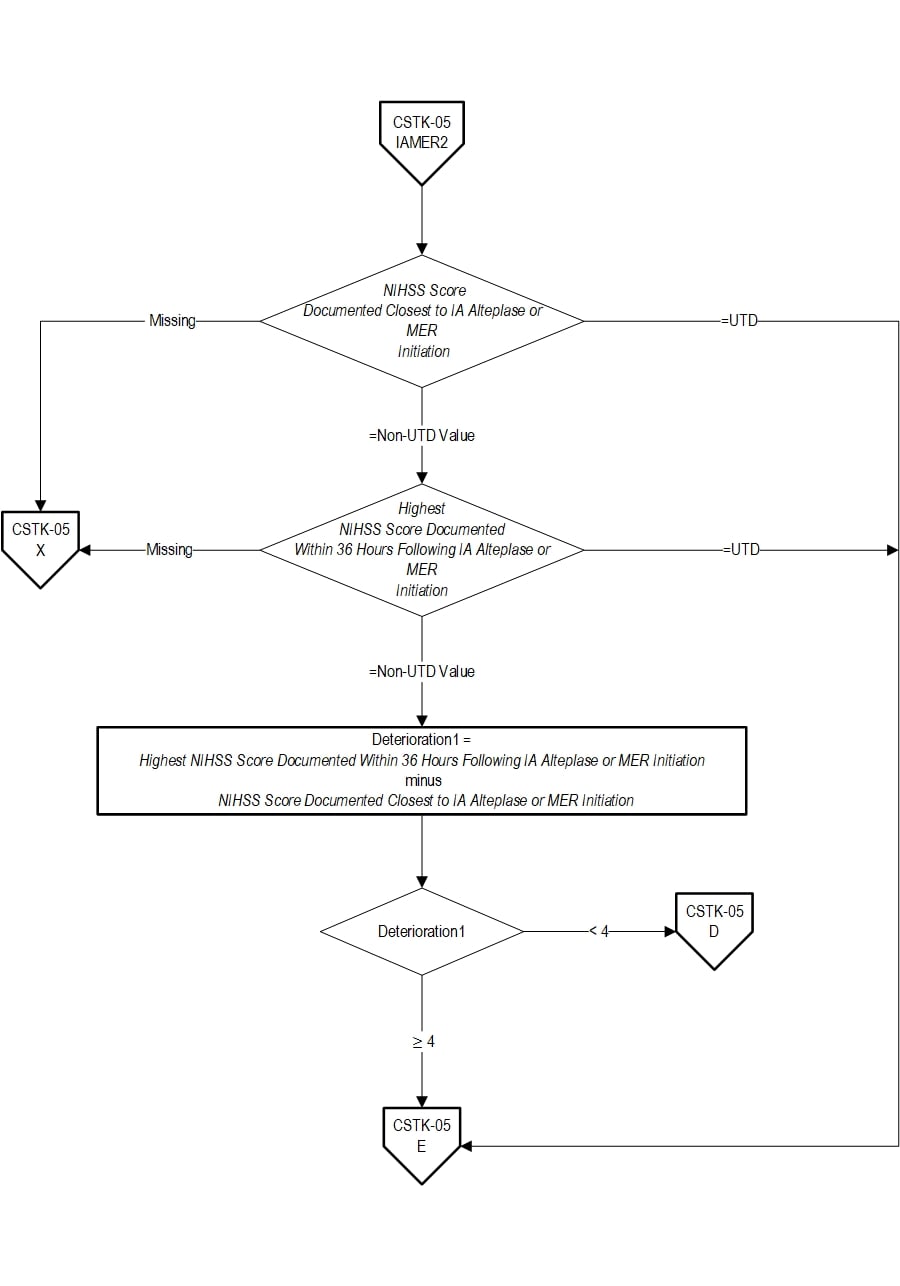
- If NIHSS Score Documented Closest to IA Alteplase or MER Initiation is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If NIHSS Score Documented Closest to IA Alteplase or MER Initiation equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If NIHSS Score Documented Closest to IA Alteplase or MER Initiation is Non-UTD value, continue processing to check Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation is Non-UTD value, continue processing to Calculate Deterioration1.
- Deterioration1 equal Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation minus NIHSS Score Documented Closest to IA Alteplase or MER Initiation.
- Proceed to Check Deterioration1.
- If Deterioration1 is less than 4, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Deterioration1 is equal or greater than 4, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
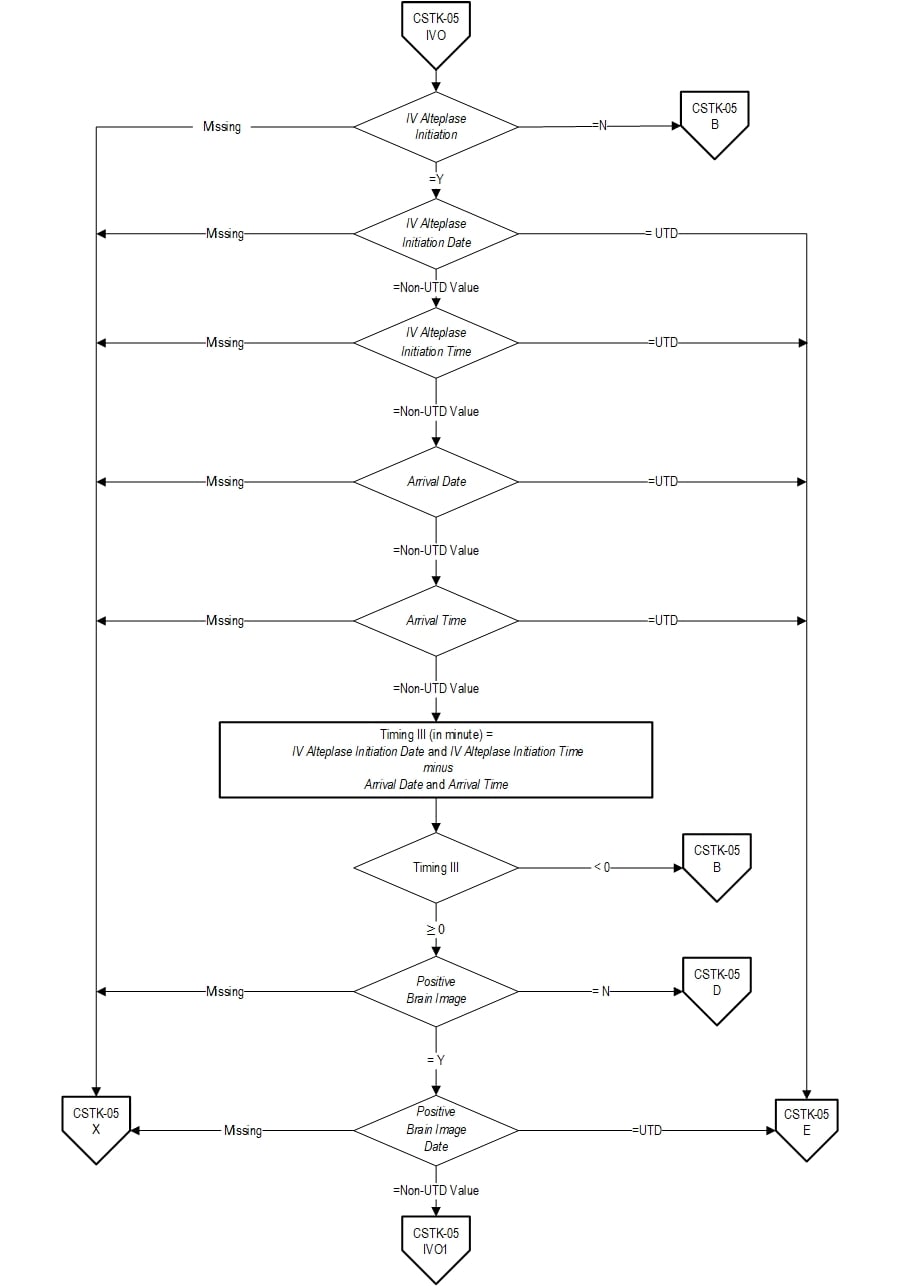
- If IV Alteplase Initiation is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If IV Alteplase Initiation equals N, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If IV Alteplase Initiation equals Y, continue processing to check IV Alteplase Initiation Date.
- If IV Alteplase Initiation Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If IV Alteplase Initiation Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If IV Alteplase Initiation Date is Non-UTD value continue processing and proceed to check IV Alteplase Initiation Time.
- If IV Alteplase Initiation Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If IV Alteplase Initiation Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If IV Alteplase Initiation Time is Non-UTD value continue processing to check Arrival Date.
- If Arrival Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Arrival Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Arrival Date is Non-UTD value continue processing and proceed to check Arrival Time.
- If Arrival Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Arrival Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Arrival Time is Non-UTD value continue processing to calculate Timing III.
- Timing III (in minute) equal IV Alteplase Initiation Date and IV Alteplase Initiation Time minus Arrival Date and Arrival Time.
- Proceed to Check Timing III (in minutes).
- If Timing III is less than 0 minutes, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If Timing III is equal or greater than 0 minutes, continue processing and proceed to check Positive Brain Image.
- If Positive Brain Image is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image equals N, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Positive Brain Image equals Y, continue processing to check Positive Brain Image Date.
- If Positive Brain Image Date is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image Date equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Positive Brain Image Date is Non-UTD value continue processing and proceed to check Positive Brain Image Time.
- If Positive Brain Image Time is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Positive Brain Image Time equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Positive Brain Image Time is Non-UTD value continue processing to calculate Timing IV.
- Timing IV (in minute) equal Positive Brain Image Date and Positive Brain Image Time minus IV Alteplase Initiation Date and IV Alteplase Initiation Time.
- Proceed to Check Timing IV (in minutes).
- If Timing IV is less than 0 minutes, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Proceed to Step 38.
- If Timing IV is greater than 2160 minutes, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Timing IV is equal or greater than 0 minutes and equal or less than 2160 minutes, continue processing and proceed to check NIHSS Score Documented Closest to IV Alteplase Initiation.
- If NIHSS Score Documented Closest to IV Alteplase Initiation is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If NIHSS Score Documented Closest to IV Alteplase Initiation equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If NIHSS Score Documented Closest to IV Alteplase Initiation is Non-UTD value, continue processing to check Highest NIHSS Score Documented Within 36 Hours Following IV Alteplase Initiation.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Proceed to Step 38.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation equals UTD, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
- If Highest NIHSS Score Documented Within 36 Hours Following IA Alteplase or MER Initiation is Non-UTD value, continue processing to Calculate Deterioration2.
- Deterioration2 equal Highest NIHSS Score Documented Within 36 Hours Following IV Alteplase Initiation minus NIHSS Score Documented Closest to IV Alteplase Initiation.
- Proceed to Check Deterioration2.
- If Deterioration2 is less than 4, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Proceed to Step 38.
- If Deterioration2 is equal or greater than 4, the case will proceed to a Measure Category Assignment of E and will be in the numerator population. Proceed to Step 38.
39. Check Overall Rate Category Assignment.
- If Overall Rate Category Assignment equals X, Set the Measure Category Assignment for strata measures CSTK-05a and CSTK-05b = ‘X’. Stop processing.
- If Overall Rate Category Assignment equals B, Set the Measure Category Assignment for strata measures CSTK-05a and CSTK-05b = ‘B’. Stop processing.
- If Overall Rate Category Assignment equals D or E, continue processing to check ICD-10-PCS Principal or Other Procedure Codes.
- If at least one of the ICD-10-PCS Principal or Other Procedure Codes is on Table 8.1b, Set Measure Category Assignment for strata measure CSTK-05b equal Measure Category Assignment for measure CSTK-05. Stop processing.
- If none of the ICD-10-PCS Principal or Other Procedure Codes are on Table 8.1b, continue processing to check IA Route of Alteplase Administration.
- If IA Route of Alteplase Administration equals Y, Set Measure Category Assignment for strata measure CSTK-05b equal Measure Category Assignment for measure CSTK-05. Stop processing.
- If IA Route of Alteplase Administration equals N, Set Measure Category Assignment for strata measure CSTK-05a equal Measure Category Assignment for measure CSTK-05. Stop processing.
LICENSE FOR USE OF CURRENT PROCEDURAL TERMINOLOGY, FOURTH EDITION (“CPT®”)
CPT® only copyright 2026 American Medical Association. All rights reserved. CPT® is a registered trademark of the American Medical Association.
You, your employees and agents are authorized to use CPT® only as contained in The Joint Commission performance measures solely for your own personal use in directly participating in healthcare programs administered by The Joint Commission. You acknowledge that the American Medical Association (“AMA”) holds all copyright, trademark and other rights in CPT®.
Any use not authorized herein is prohibited, including by way of illustration and not by way of limitation, making copies of CPT® for resale and/or license, transferring copies of CPT® to any party not bound by this Agreement, creating any modified or derivative work of CPT®, or making any commercial use of CPT®. License to use CPT® for any use not authorized herein must be obtained through the American Medical Association, Intellectual Property Services, AMA Plaza, 330 North Wabash Avenue, Suite 39300, Chicago, Illinois 60611-5885. Applications are available at the American Medical Association Web site, www.ama- assn.org/go/cpt.
U.S. Government Rights This product includes CPT® which is commercial technical data, which was developed exclusively at private expense by the American Medical Association, 330 North Wabash Avenue, Chicago, Illinois 60611. The American Medical Association does not agree to license CPT® to the Federal Government based on the license in FAR 52.227-14 (Data Rights - General) and DFARS 252.227-7015 (Technical Data - Commercial Items) or any other license provision. The American Medical Association reserves all rights to approve any license with any Federal agency.
Disclaimer of Warranties and Liabilities. CPT® is provided “as is” without warranty of any kind, either expressed or implied, including but not limited to the implied warranties of merchantability and fitness for a particular purpose. Fee schedules, relative value units, conversion factors and/or related components are not assigned by the AMA, are not part of CPT®, and the (AMA is not recommending their use. The AMA does not directly or indirectly practice medicine or dispense medical services. The responsibility for the content of this product is with The Joint Commission, and no endorsement by the AMA is intended or implied. The AMA disclaims responsibility for any consequences or liability attributable to or related to any use, non-use, or interpretation of information contained or not contained in this product.
This Agreement will terminate upon notice if you violate its terms. The AMA is a third party beneficiary to this Agreement.
Should the foregoing terms and conditions be acceptable to you, please indicate your agreement and acceptance by clicking below on the button labeled “accept”.