Measure Information Form
Version 2027A
Measure Information Form
AF is also an important risk factor for stroke. Furthermore, a prior stroke or transient ischemic attack (TIA) are among a limited number of predictors of high stroke risk within the population of patients with atrial fibrillation. Nonparoxysmal AF compared to paroxysmal AF has been associated with a higher risk of stroke in this patient population. Therefore, much emphasis has been placed on identifying methods for preventing recurrent ischemic stroke as well as preventing first stroke. Prevention strategies focus on the modifiable risk factors such as hypertension, smoking, and atrial fibrillation.
Analysis of placebo-controlled clinical trials (e.g., AFASAK, BAATAF, SPAF, CAFA, SPINAF, EAFT) investigating the efficacy of warfarin in the primary prevention of thromboembolic stroke found that warfarin reduced the relative risk of thromboembolic stroke by about two-thirds (RR ≈ 0.3–0.4) for AF patients. In more recent years, direct oral anticoagulant agents have been developed and approved by the FDA for stroke prevention. The AHA/ASA guidelines now prefer direct oral anticoagulant medications over warfarin for secondary prevention in ischemic stroke patients with AF/flutter, (Kleindorfer, D., et al., 2021). Globally, the use of direct oral anticoagulant medications has continued to increase since 2018, and the prevalence of vitamin K antagonist use decreased. Clinicians still treat about 10 percent of patients with antiplatelet medications only, (Ibid.). Type Of Measure: Process Improvement Noted As: Increase in the rateIncluded Populations: Not applicable Excluded Populations: None Data Elements:Denominator Statement: Ischemic stroke patients with documented atrial fibrillation/flutter.
Included Populations:Excluded Populations:
- Discharges with an ICD-10-CM Principal Diagnosis Code for ischemic stroke as defined in Appendix A, Table 8.1
- Patients with documented Atrial Fibrillation/Flutter
Data Elements:
- Patients less than 18 years of age
- Patients who have a Length of Stay greater than 120 days
- Patients with Comfort Measures Only documented
- Patients enrolled in clinical trials
- Patients admitted for Elective Carotid Intervention
- Patients discharged to another hospital
- Patients who left against medical advice
- Patients who expired
- Patients discharged to home for hospice care
- Patients discharged to a health care facility for hospice care
- Patients with a documented Reason For Not Prescribing Anticoagulation Therapy
- Campbell, L. A., Ammon, J. P., Kombathula, R., Muhammad, N., & Jackson, C. D. (2025). New atrial fibrillation guideline: Modify risk, control rhythm, prevent progression. Cleveland Clinic Journal of Medicine, 92 (5), 291–296. https://doi.org/10.3949/ccjm.92a.24067
- January, C. T., Wann, S., Calkins, H., Chen, L. Y., Cigarroa, J. E., Cleveland, J. C., Ellinor, P. T., … (2019). 2019 AHA/ACC/HRS focused update of the 2014 AHA/ACC/HRS guideline for the management of patients with atrial fibrillation: A report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines and the Heart Rhythm Society. Circulation, 140 (2), e125–e151.
- Kleindorfer, D. O., Towfighi, A, Chaturvedi, S., Cockroft, K. M., Gutierrez, J., Lombardi-Hill, D., Kamel, H., Kernan, W. N., Kittner, S. J., Leira, E. C., Lennon, O., Meschia, J. F., Nguyen, T. N., Pollak, P. M., Santangeli, P., Sharrief, A. Z., Smith, S. C., Jr., Turan, T. N., & Williams, L. S. (2021). Guideline for the prevention of stroke in patients with stroke and transient ischemic attack: A guideline from the American Heart Association/American Stroke Association. Stroke, 52 (7), e364–e467.
- Kornej, J., Börschel, C. S., Benjamin, E. J., & Schnabel, R. B. (2020). Epidemiology of atrial fibrillation in the 21st century: Novel methods and new insights. Circulation Research, 127 (1), 4–20.
- Martin, S. S., Aday, A. W., Allen, N. B., Almarzooq, Z. I., Anderson, C. A. M., Arora, P., … Palaniappan, L. P. (2025). 2025 heart disease and stroke statistics: A report of US and global data from the American Heart Association. Circulation, 151, e333–e334.
- Palaniappan, L. P., Allen, N. B., Almarzooq, Z. I., Anderson, C. A. M., Arora, P., Avery, C. L., Baker-Smith, C. M., Bansal, N., Currie, M. E., Earlie, R. S., Fan, W., Fetterman, J. L., Barone Gibbs, B., Heard, D. G., Hiremath, S., Hong, H., Hyacinth, H. I., Ibeh, C., Jiang, T., … Khan, S. S. (2026). 2026 heart disease and stroke statistics: A report of U.S. and global data from the American Heart Association. Circulation. Advance online publication. https://doi.org/10.1161/CIR.0000000000001412
- Powers, W. J., Rabinstein, A. A., Ackerson, T., Adeoye, O. M., Bambakidis, N. C., Becker, K., Biller, J., et al., on behalf of the American Heart Association Stroke Council. (2018). 2018 guidelines for the early management of patients with acute ischemic stroke: A guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 49, e10–e11, e26–e30.
- Powers, W. J., Rabinstein, A. A., Ackerson, T., Adeoye, O. M., Bambakidis, N. C., Becker, K., Biller, J., et al. (2019). Guidelines for the early management of patients with acute ischemic stroke: 2019 update to the 2018 guidelines for the early management of acute ischemic stroke—A guideline for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 50 (12), e344–e418.
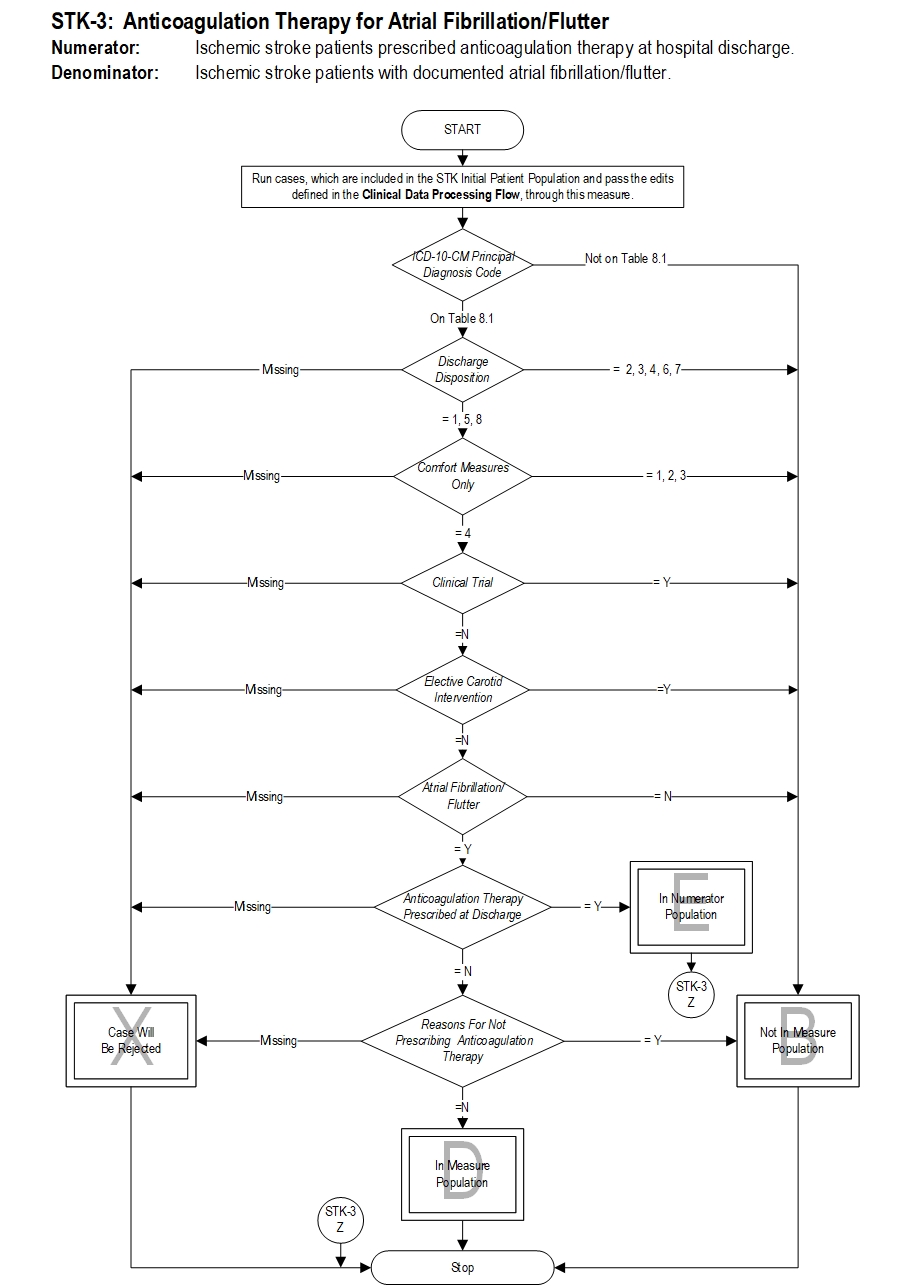
STK-3: Algorithm Narrative
STK-3: Anticoagulation Therapy for Atrial Fibrillation/Flutter Numerator: Ischemic stroke patients prescribed anticoagulation therapy at hospital discharge.
Denominator: Ischemic stroke patients with documented atrial fibrillation/flutter.
1. Start processing. Run cases, which are included in the Stroke Initial Patient Population and pass the edits defined in the Clinical Data Processing Flow, through this measure.
2. Check ICD-10 CM Principal Diagnosis codes
- If none of the ICD-10 CM Principal Diagnosis codes are on Table 8.1, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If at least one of the ICD-10 CM Principal Diagnosis codes is on Table 8.1, continue processing and proceed to check Discharge Disposition.
- If Discharge Disposition is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Discharge Disposition equals 2, 3, 4, 6 or 7, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Discharge Disposition equals 1, 5 or 8, continue processing and proceed to check Comfort Measures Only.
- If Comfort Measures Only is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Comfort Measures Only equals 1, 2 or 3, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Comfort Measures Only equals 4, continue processing and proceed to check Clinical Trial.
- If Clinical Trial is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Clinical Trial equals Y, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Clinical Trial equals N, continue processing and proceed to check Elective Carotid Intervention.
- If Elective Carotid Intervention is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Elective Carotid Intervention equals Y, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Elective Carotid Intervention equals N, continue processing and proceed to check Atrial Fibrillation/Flutter.
- If Atrial Fibrillation/Flutter is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Atrial Fibrillation/Flutter equals N, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Atrial Fibrillation/Flutter equals Y, the case will proceed to check Anticoagulation Therapy Prescribed at Discharge.
- If Anticoagulation Therapy Prescribed at Discharge is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Anticoagulation Therapy Prescribed at Discharge equals Y, the case will proceed to a Measure Category Assignment of E and will be in the Numerator Population. Stop processing.
- If Anticoagulation Therapy Prescribed at Discharge equals N, the case will proceed to check Reasons For Not Prescribing Anticoagulation Therapy.
- If Reasons For Not Prescribing Anticoagulation Therapy is missing, the case will proceed to a Measure Category Assignment of X and will be rejected. Stop processing.
- If Reasons For Not Prescribing Anticoagulation Therapy equals Y, the case will proceed to a Measure Category Assignment of B and will not be in the Measure Population. Stop processing.
- If Reasons For Not Prescribing Anticoagulation Therapy equals N, the case will proceed to a Measure Category Assignment of D and will be in the Measure Population. Stop processing.
LICENSE FOR USE OF CURRENT PROCEDURAL TERMINOLOGY, FOURTH EDITION (“CPT®”)
CPT® only copyright 2026 American Medical Association. All rights reserved. CPT® is a registered trademark of the American Medical Association.
You, your employees and agents are authorized to use CPT® only as contained in The Joint Commission performance measures solely for your own personal use in directly participating in healthcare programs administered by The Joint Commission. You acknowledge that the American Medical Association (“AMA”) holds all copyright, trademark and other rights in CPT®.
Any use not authorized herein is prohibited, including by way of illustration and not by way of limitation, making copies of CPT® for resale and/or license, transferring copies of CPT® to any party not bound by this Agreement, creating any modified or derivative work of CPT®, or making any commercial use of CPT®. License to use CPT® for any use not authorized herein must be obtained through the American Medical Association, Intellectual Property Services, AMA Plaza, 330 North Wabash Avenue, Suite 39300, Chicago, Illinois 60611-5885. Applications are available at the American Medical Association Web site, www.ama- assn.org/go/cpt.
U.S. Government Rights This product includes CPT® which is commercial technical data, which was developed exclusively at private expense by the American Medical Association, 330 North Wabash Avenue, Chicago, Illinois 60611. The American Medical Association does not agree to license CPT® to the Federal Government based on the license in FAR 52.227-14 (Data Rights - General) and DFARS 252.227-7015 (Technical Data - Commercial Items) or any other license provision. The American Medical Association reserves all rights to approve any license with any Federal agency.
Disclaimer of Warranties and Liabilities. CPT® is provided “as is” without warranty of any kind, either expressed or implied, including but not limited to the implied warranties of merchantability and fitness for a particular purpose. Fee schedules, relative value units, conversion factors and/or related components are not assigned by the AMA, are not part of CPT®, and the (AMA is not recommending their use. The AMA does not directly or indirectly practice medicine or dispense medical services. The responsibility for the content of this product is with The Joint Commission, and no endorsement by the AMA is intended or implied. The AMA disclaims responsibility for any consequences or liability attributable to or related to any use, non-use, or interpretation of information contained or not contained in this product.
This Agreement will terminate upon notice if you violate its terms. The AMA is a third party beneficiary to this Agreement.
Should the foregoing terms and conditions be acceptable to you, please indicate your agreement and acceptance by clicking below on the button labeled “accept”.